
OCD Help From a Muslim Therapist
About Dr. Aisha Chaudhry
Dr. Aisha Chaudhry is an Aalimah and Muslim therapist. She specializes in trauma which often looks like depression, anxiety including OCD, intrusive thoughts, health anxiety, and panic. She has a special interest in helping clients learn how to calm the body through a combination of neural informed therapies, Internal Family Systems, CBT, and Exposure-Response Prevention. For clients looking for integrated therapy, a holistic approach is available.
What is OCD?
Obsessive-compulsive disorder (OCD) is a disorder in which people have recurring, unwanted thoughts, ideas, images, or sensations (obsessions) that make them feel driven to do something repetitively (compulsions). Repetitive behaviors, such as hand washing, checking on things, or cleaning, can significantly interfere with a person’s daily activities and social interactions.
It is very normal for distressing, repetitive thoughts to enter anyone’s mind, at any time. The difference is that they typically don’t remain in the mind for too long and they do not cause distress to the point of disrupting daily life.
Individuals who suffer from OCD have thoughts that are persistent and, as a result, they begin to engage in rigid behaviors; they often will have the family engaging in their behaviors as well because it’s easier to deal with if they just comply. When a person suffers from OCD, the distress is so great that they find themselves consumed for sometimes hours in a day, or many hours over the course of a day, trying to gain relief or satisfaction from the distressing thoughts or images. They may feel not performing behaviors (rituals) is nearly not an option, or if they do manage to ignore the thoughts and move on, they often suffer through it. For some individuals, they do not engage in an external behavior, or perhaps they are unaware of that external behavior. For example, if a distressing, intrusive thought comes, they may mentally negate it – while showing nothing externally to witness. For this reason, individuals may suffer for quite a long time without anyone knowing that anything is actually occurring. Sometimes individuals suffering aren’t aware at all that they are suffering. They may have strong beliefs that what they are doing is correct and may even see it as being the best version of themselves.
The Think-About
Struggling with OCD can feel like being stuck on a roundabout where some cars are able to exit the roundabout, but individuals with OCD cannot without great distress. They might look at the exits of the roundabout and wish to exit, but they just keep circling around and around the center, which I call the theme. It feels like a loop, and the sufferer really struggles to get off. I call this roundabout a “think-about” because the individual keeps thinking and thinking, and they get enough reassurance and satisfaction to get off, but then after a short period of time, they find themselves right back on that same think-about.
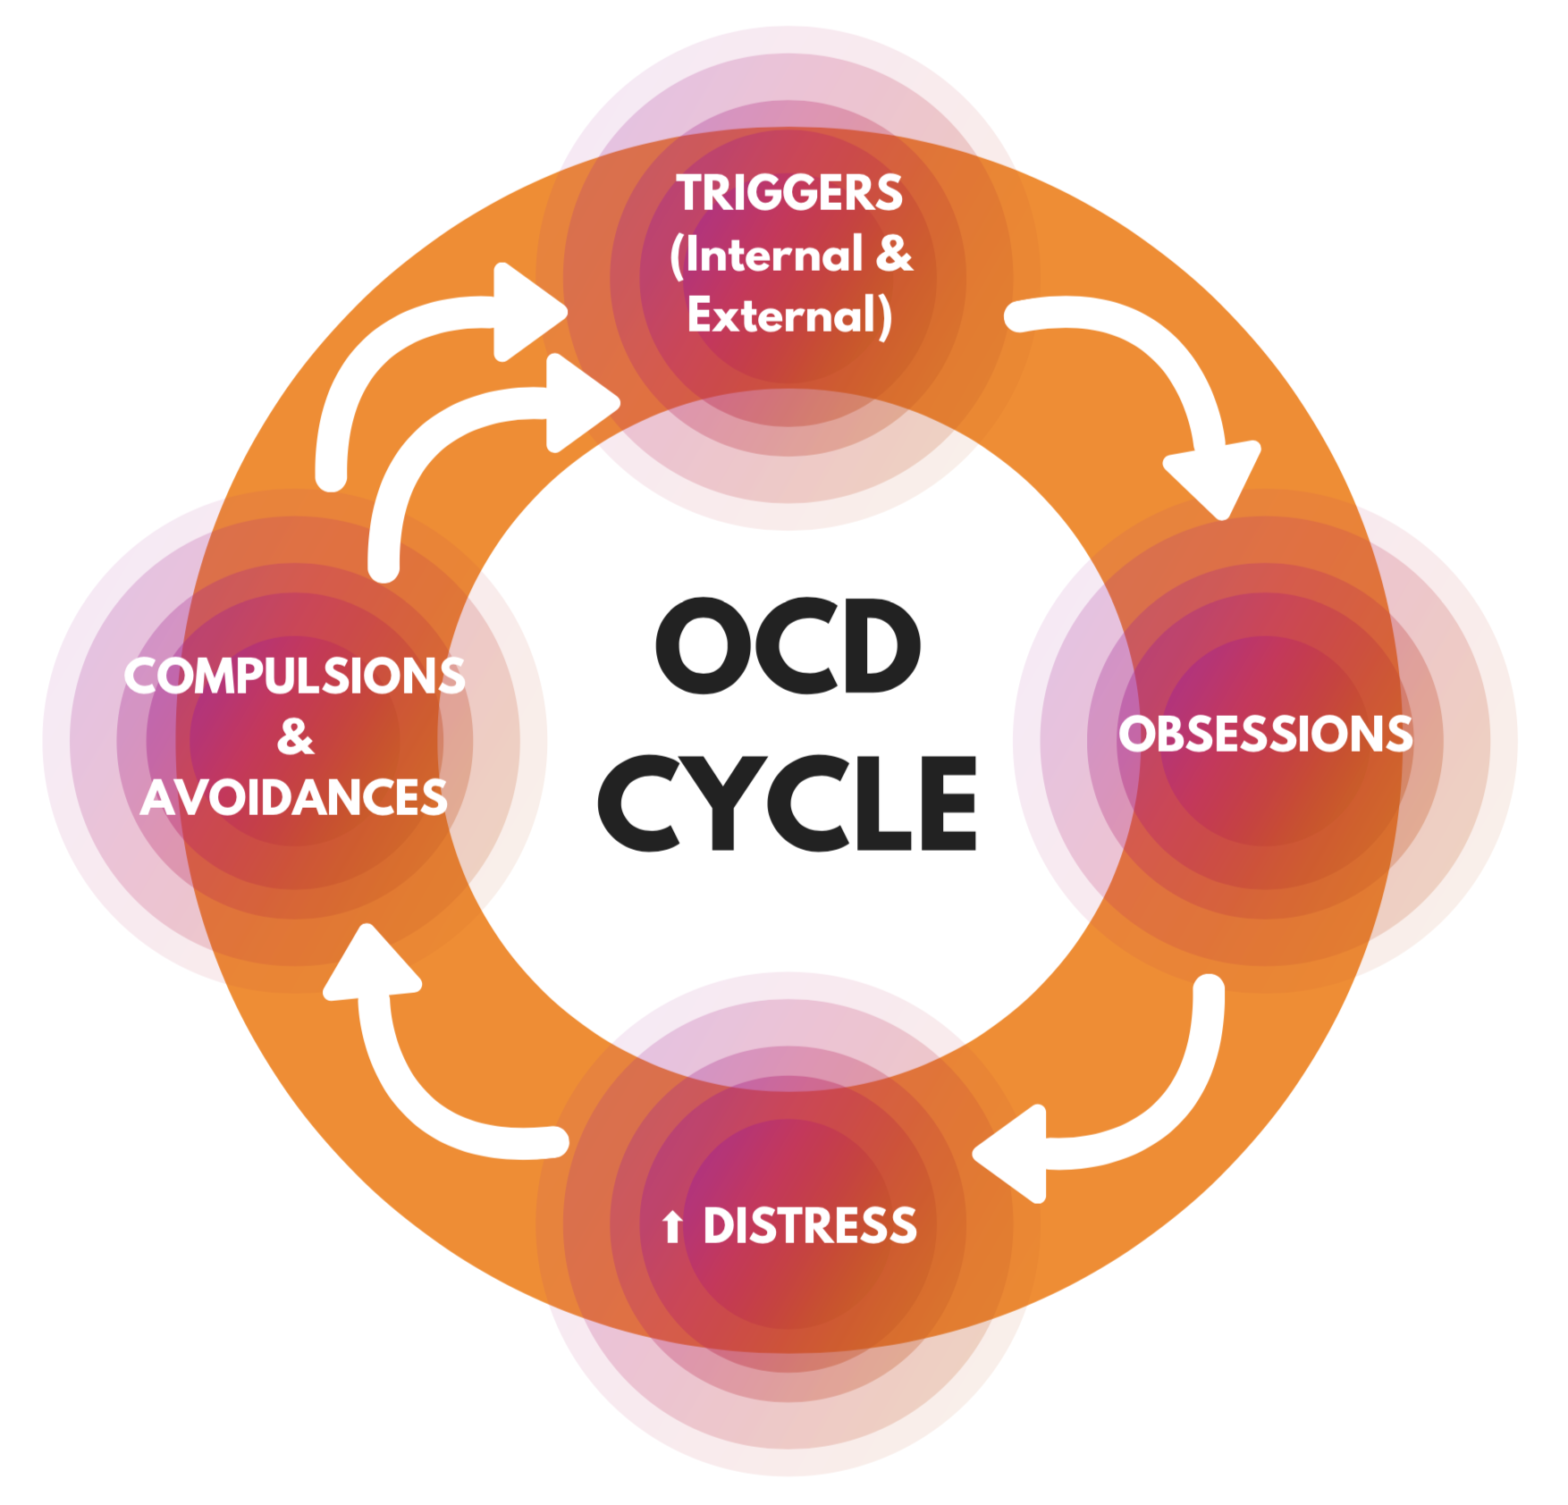
Getting help with OCD from a Muslim therapist can be helpful because we can learn how to get off of this negative think-about and onto a healthier one, which incorporates moderate views of Islam and other attributes of Allah in a more balanced way. Allah (subhanahu wa ta’ala) isn’t just the One who will punish us. He is so many other things, like the One who has mercy, provides, nourishes, and loves us. Getting help with OCD from a Muslim therapist will help you to balance these views, in sha Allah.
What are Obsessions?
Obsessions are recurrent and persistent thoughts, impulses, or images that cause distressing emotions such as anxiety or disgust. Many people with OCD recognize that the thoughts, impulses, or images are a product of their minds and are excessive or unreasonable. However, the distress caused by these intrusive thoughts cannot be resolved by logic or reasoning. Most people with OCD try to ease the distress of the obsessions with compulsions, ignore or suppress the obsessions, or distract themselves with other activities.
A Few Broad Areas of Obsessions:
- Religious or moral scrupulosity
- Relationship obsessions (current or previous)
- Obsessional jealousy
- Fear of making a mistake while reading the Quran
- Uncertainty about not being clean (for prayers, reading, etc.)
- Uncertainty of completeness or correctness
- Fear of not saying or doing something just right
- Fear that not saying a particular dua or phrase will cause harm
- Fear of getting contaminated by people or the environment
- Fear of food getting contaminated
- Obsessive worries about food being halal or haram
- Disturbing sexual and/or violent thoughts or images
- Fear of harming self or someone else (stabbing, killing, running over, punching, kicking)
- Excessively doubting oneself or others’ intentions about anything
- Fear of blurting out obscenities or insults
- Extreme concern with order, symmetry, or precision
- Recurrent intrusive thoughts of sounds, images, words, or numbers
- Fear of losing or discarding something important
- Constant thoughts about a particular part of the body
- Excessive concern with having an illness
- Excessive worry about breaking rules
- Repeating numbers or phrases
What Individuals With OCD Say
OCD can appear in one specific area or many areas of one’s life. Below are just examples of what clients might say, to give you an idea of what an obsessive thought or fear might sound like. Please keep in mind that everyone has the same thoughts, but an individual with OCD struggles with those thoughts, believing they are real or valid to the point of engaging in other behaviors to calm down that fear or thought (known as a compulsion or ritual; we will talk more about that coming up). OCD help from a Muslim therapist will be beneficial because all of my clients are Muslims, and I have the benefit of knowing exactly where some of the issues are religiously, culturally, and interpersonally.
Clients often say things like:
- I have blasphemous thoughts about Allah or the Prophet ﷺ and I may go to Hell.
- I don’t think Allah will forgive me.
- If I don’t pray just right I will go to Hell, and I don’t want to be sinful.
- I think I need to do everything 3 times or I’ll be sinful or not accepted.
- I am never really sure if I did things right.
- I don’t know if I have wudhu or ghusl.
- Maybe I didn’t clean myself properly.
- Maybe I made a mistake in reading Quran and I should start over.
- Does my spouse or family really love me?
- Do I really love my spouse or family?
- Did I marry the right person, or is this the right person to marry?
- Maybe I need to fix this a bit more.
- I need a lot of reassurance from others or my spouse. I am not sure how others really feel.
- I have too many thoughts and sometimes I just want to drown them out.
- I have disturbing, violent thoughts or images.
- I have intrusive sexual, sexually aggressive, or seemingly inappropriate thoughts or images.
- I have a lot of very embarrassing thoughts and sensations happening in my body.
- I have intrusive doubts about my sexual orientation.
- I am afraid I might hurt someone or myself.
- I feel like I am never saying my prayers correctly.
- I never feel sure I’ve cleaned myself properly.
- I am not sure if I have wudhu.
- I check and often recheck things a lot to make sure it’s off, a person is still alive, or a person is unharmed.
- I have thoughts or images of stabbing someone, running over someone, or pushing, kicking, punching someone.
- I think someone will get hurt or ill and it’ll be my fault.
- I need to make sure everyone is safe, because if someone were to get harmed or sick, it will be my fault and I can’t bear that.
- I need to make sure there are no germs, residues of chemicals, or contaminants that might make me or someone else ill or poisoned.
- I count, line up, repeat, re-read, make lists, make things symmetrical, keep things in a certain way.
- I am sure I’ve committed sins that Allah won’t forgive.
- Maybe I didn’t ask for forgiveness properly or sincerely enough.
- Maybe because of these thoughts I am going to be punished.
- Maybe my spouse is in love with someone else or not in love with me.
- Maybe my spouse wishes he had married someone else.
- What if I made a mistake and now my children and their future are at stake?
- Do I owe money to people?
- Did I steal something because of a coupon, discount, or misunderstanding of a sale or promotion?
- Did I pull one over on someone?
- Did I cheat on my taxes?
- Is this part of my face symmetrical compared with the other?
- I just need to fix the nails or skin on my fingers or toes (leading to biting, picking, with and without tools).
- Maybe this hair is not matching with the other (leading to hair pulling or perhaps a part of safety-seeking).
- I need to tell someone I did something wrong or broke a rule.
Don’t Believe Everything You Think
Just because you think it or fear it does not make it true. Sometimes the brain has a stubborn desire to hold on to a particular belief, particularly if the stakes seem high. And sometimes it’s as though images of random frightening or repulsive things flash through the mind. What do you say about yourself when these thoughts and images come? It is hard to bear, so we go into overdrive to stop it all.
We will work fervently to ‘make sure’ something doesn’t happen or that we are not bad or sinful.
Those inner thoughts can feel like a bully or the voice of an inner critic. Dr. Aisha can help you learn how to take charge of your thoughts instead of thoughts taking charge of you, your life, and your family’s life.
Schedule AppointmentAbout Compulsions
Compulsions, also called rituals, are usually performed in order to reduce distress related to an obsession. Compulsions are often repeated either by certain outward actions or mentally. Compulsions can either be directly related or unrelated to an obsession. These compulsions can take up a significant amount of time in a person’s day, resulting in other consequences like other disorders or interruption of functioning at work, school, social, or other areas of life.
Compulsions look like: checking, seeking reassurance, redoing, rereading, making sure, getting things ‘just’ right or balanced, trying to undo what has been done, negating, and many others. OCD is unique, and what it looks like in a sufferer’s life is unique. But the core treatment for all is the same. Getting help with OCD from a Muslim therapist will be beneficial because as Muslims, we know what rituals should look like in our deen – not the ones we create ourselves.
Common Examples of Compulsions:
- Repeating ablutions (wudhu) due to feelings of incompleteness, incorrectness, or some defect in it
- Doubting if one still has ablution (wudhu) to the point that the uncertainty causes them to repeat it
- Repeatedly watching the body or things, not being sure a proper shower (ghusl) has been completed, which compels a person to repeat the ghusl or complete it in a certain way “to be sure”
- Repeating prayers (salah) or doing sajda sahw unnecessarily
- Not being certain where one is in prayer, which is not due to a neurological memory issue, so one might repeat the prayer or a part of it
- Doubting if one recited the Quran correctly and then repeating the verses or starting all over
- Repeating dhikr or tasbih because you think you didn’t do it correctly or the right number of times, often following a routine you assigned to it, until it feels just like it should be
- Thinking that something forbidden (haram) or disliked (makrooh) might have dropped into the food, which compels the person to throw the food away and start fresh
- Doubting ingredients of a food or drink product although sound opinions are given, which compels them not to purchase or consume it
- Excessive or ritualized hand washing, showering, brushing teeth, or toileting
- Repeated cleaning of household objects
- Ordering or arranging things in a particular way
- Repeatedly checking locks, switches, or appliances
- Creating lists upon lists so as not to forget, or to make sure everything is listed or organized
- Making sure mistakes are not made and even apologizing just in case
- Constantly seeking approval or reassurance
- Repeatedly counting to a certain number
- Picking skin, biting nails, pulling out hair
- Drumming, tapping, making throaty sounds
- Making sure one part of the body does not contaminate another part
- Making many doctor appointments or getting a lot of labs to make sure there is nothing wrong
- Researching or googling different topics to make sure the information is right or complete
- Repeatedly asking in different ways to make sure the person understands the question correctly, so the wrong answer or result doesn’t come
- Getting up or turning toward something the same number of times
- Getting divorced or moving out because of relationship obsessions, to prevent the spouse from getting hurt, contaminated, poisoned, or otherwise ill
- Seeking reassurance by checking a spouse’s clothing, email, browsing history, video watch history, social media accounts, or popping in at work
- Saying a particular dua or verse of Quran with the conviction that if it is not said, someone will get hurt and you will be blameworthy
- Keeping a particular routine to ‘ensure’ nothing harmful happens, with the conviction that if it’s not kept, something bad will happen and you will be blameworthy
- Doing different things to block or drown out sounds, images, or thoughts of any kind
Piety or OCD?
I do wish there was a way to definitively write down a checklist of whether it is piety or OCD. One issue is that there is a narration that, in part, says that sin is that which wavers in the soul and causes unease (Sahih Muslim 2553). On the other hand, Allah (subhanahu wa ta’ala) does not put on us more than we can bear, nor does He encourage excessive, rigid, or polarized thinking or behaviors.
Abu Hurairah (may Allah be pleased with him) reported: Some of his Companions came to the Messenger of Allah ﷺ and said, “We have thoughts that we cannot dare talk about, and we do not like that we have them or talk about them.” He said, “Have you experienced that?” They replied, “Yes.” He said, “That is clear faith.”
Sunan Abi Dawud (5111); also reported in Sahih Muslim (132)
For this reason, we have to take the whole person into consideration along with the thought and behavior processes. Getting help with OCD from a Muslim therapist will help because as Muslims, we can decipher between excessiveness, rigidity, and piety.
Rigidity often shows up in many areas of life, and with rigidity comes intolerance of oneself and others and their behaviors, as well as other emotions like anger, outbursts, overwhelm, despair, and others.
In order to differentiate whether a thought-behavior pattern is being kept out of piety or is perhaps excessive due to OCD, we need to examine the cycle in more detail. Most likely you will need help from a qualified therapist to differentiate. If you are reading through this and you’re not sure, reach out.
Please keep in mind that I usually get a lot of background information and then analyze it in totality to help you determine if you are a very pious person or if you are unfairly excessive in one area. I absolutely do not judge and wholeheartedly invite you to explore this. Understanding OCD often needs help.
- When you have the thought, how distressing is it? Does your mind try to write one outcome and ignore perspectives and possibilities?
- When you don’t engage in compulsions or rituals, what do you do or how do you cope?
- Are you engaging in safety behaviors such as avoiding, seeking reassurance, checking, repeating, etc.? Ask yourself what you do as a result of these thoughts.
- Are people at work, school, family, or social domains noticing something may not be ok or perhaps suggesting you should talk to someone?
- Are you asking other people to engage in your safety behaviors or rituals (to make sure everything will be ok)?
- Do you spend a lot of time trying to get through the distressing thoughts, images, or behavior?
- Are you feeling negative, disempowering emotions as a result of the thoughts, images, or behaviors?
- Would you say that you are equally pious in other areas of your life except for these couple of things? For example, a person does not eat halal, zabiha food regularly or doesn’t mind that much, but on the other hand struggles with prayers or wudhu and is overly meticulous in comparison.
- Are others feeling it is really difficult to live and be around you?
- Ask yourself what will happen if you do not engage in that safety, ritualistic behavior. What comes up for you?
Diagnosing OCD
To diagnose OCD, I use the criteria specified by the American Psychiatric Association (APA). Additionally, I use one or more assessment instruments to create a baseline of symptoms and their severity. This helps us know where we are starting so that we know if we are progressing. However, as a Muslim therapist who has experience in treating OCD, I will look at the totality of a person in relation to religious practices. Not all clinicians will know, without lengthy explanations, what would be considered excessive or creating a hardship for oneself.
In summary, the DSM-5-TR criteria for OCD (F42.2) are:
Obsessions, compulsions, or both
Obsessions are recurring, unwanted thoughts, urges or images that feel intrusive and usually cause marked anxiety or distress, which the person tries to ignore, push away or neutralize. Compulsions are repeated behaviors (such as washing, ordering or checking) or mental acts (such as praying, counting or repeating words silently) that the person feels driven to do in response to an obsession or rigid rules, to reduce distress or prevent a feared outcome, even though they are not realistically connected to it or are clearly excessive.
Time-consuming or impairing
The obsessions or compulsions take up a lot of time (for example, more than an hour a day) or cause significant distress or difficulty at home, work, school or in relationships.
Not due to a substance or medical condition
The symptoms are not caused by a medication, drug or another medical condition.
Not better explained by another condition
The symptoms are not better explained by another mental health condition, such as generalized anxiety, body dysmorphic disorder, hoarding, hair pulling, skin picking, illness anxiety, depression-related guilty rumination or a psychotic disorder.
To be specified:
Summarized in plain language from the American Psychiatric Association’s DSM-5-TR. Only a qualified professional can make a diagnosis.
Treating OCD
Clients with OCD who seek treatment will often experience improvements in their quality of life across all domains. For example, people who were previously late, lacking in focus, losing relationships, avoiding events, struggling in relationships, etc. may notice they improve their functioning and are able to reengage in areas of life they value, and improve their relationships with people and with ideas, which often helps them improve their spirituality and relationship with Allah (subhanahu wa ta’ala).
Several types of therapies may be used to help clients with OCD. As a Muslim therapist working with Muslim clients, per my client’s comfort level, I offer an integrated therapy helping them with Islamic principles and values that most find liberating. Please note that clients absolutely have the option of electing therapy without Islamic principles and values.
Cognitive Behavioral Therapy (CBT)
Cognitive behavioral therapy (CBT) is a form of psychological treatment that has been demonstrated to be effective for a range of problems including depression, anxiety disorders, alcohol and drug use problems, marital problems, eating disorders, and severe mental illness. Numerous research studies suggest that CBT leads to significant improvement in functioning and quality of life. In many studies, CBT has been demonstrated to be as effective as, or more effective than, other forms of psychological therapy or psychiatric medications.
There are many types of modalities or techniques used in CBT, but the technique used to treat OCD is Exposure and Response Prevention (ERP). ERP is the gold standard treatment for OCD and is excellent when enhanced or integrated with other therapies like Mindfulness, which includes Acceptance and Commitment Therapy (ACT). Regardless of the integration of other therapies into the main treatment, ERP must be a part of the foundational therapy. The basic principles of ERP include the following:
- Obsessions, compulsions, triggers, and safety behaviors are identified and ranked in terms of distress.
- Clients will be exposed to feared situations or images related to their obsessions, which will elicit anxiety.
- Clients are instructed to avoid the compulsive behaviors, rituals, and safety behaviors (hence the response prevention part of the treatment name).
- The client stays with the anxiety-provoking situation, while witnessing that nothing terrible is happening as a result of not trying to control, prevent, or alter the feared outcome.
- The mind and body will learn that thoughts are just thoughts and not necessarily reality, which helps the nervous system and mind develop a healthier thought-response pattern.
- Anxiety due to the specified trigger will shift as exposures are repeated and no compulsions, rituals, or safety behaviors are engaged in.
Clients will learn that they can cope without relying on trying to alter, change, or control circumstances and that whatever comes up can be dealt with without engaging in those compulsions, rituals, or safety behaviors. Even if anxiety does come around, it can be better managed.
For religious OCD, exposures are designed to stay within Islamic boundaries and never ask you to act against your faith.
Medication
A class of medications known as selective serotonin reuptake inhibitors (SSRIs), typically used to treat depression, can also be effective in the treatment of OCD. The SSRI dosage used to treat OCD is commonly higher than that used to treat depression. Clients who do not respond to one SSRI medication sometimes respond to another. Other psychiatric medications can also be effective. Noticeable benefit often takes eight to twelve weeks.
Clients with mild to moderate OCD symptoms are typically treated with either CBT or medication depending on patient preference, the client’s cognitive abilities and level of insight, the presence or absence of associated psychiatric conditions, and treatment availability. For severe OCD symptoms, a combination of CBT and medication is often recommended.
Disclaimer: I am not recommending you take a medication or remove your current medication. Please talk to your prescriber to see if the medications are right for you.
- About 7 out of 10 people with OCD benefit from medication, ERP, or both.
- A higher dose is often necessary before some medications start working for OCD.
- Taking benzodiazepines like Xanax can become a compulsion, and they carry a risk of dependence. Your brain may learn that the only way to reduce anxiety is to take this type of medication.
- Medication and treatment together can often make a big difference in reducing symptoms of OCD and anxiety.
Medications commonly used for OCD (as listed by the International OCD Foundation) include fluvoxamine (Luvox®), fluoxetine (Prozac®), sertraline (Zoloft®), paroxetine (Paxil®), citalopram (Celexa®), escitalopram (Lexapro®), clomipramine (Anafranil®) and venlafaxine (Effexor®). Doses for OCD are set by your prescriber. See the IOCDF medication guide.
Some psychiatrists choose to add what’s called an atypical antipsychotic medication if a person is struggling to respond to treatment.
NOTE: I do not prescribe medication, but I do request clients who are finding treatment too difficult due to the severity to seek help from a psychiatrist for medication while continuing therapy together. For many clients, ERP alone brings strong improvement, and medication can be very helpful when symptoms are severe.
Neurosurgical Treatments
Neurosurgical treatment (e.g., deep brain stimulation, anterior capsulotomy) is sometimes considered in severe cases that have not responded to other treatments.
Deep brain stimulation is used in some people with severe OCD that is not responding to other treatments. Some studies suggest that anterior capsulotomy, a surgical procedure, can also be effective for carefully selected, treatment-resistant cases. These options are rare and are only considered by specialized medical teams.
Family Members & Friends Support
In people with OCD who live with family or caregivers, enlisting the support of caregivers to help with exposure practice at home is recommended. I often encourage individuals to have a buddy in order to help make sure they do not engage in safety behaviors, as well as to instruct them not to reassure, by educating them about these processes.
It is important for family members and friends not to allow themselves and their routines to be changed due to OCD. Sometimes individuals with OCD will create a routine or habits in the home that support their level of comfort, and this can be extremely disruptive to others.
It is also important for family members not to reassure or validate thoughts a person with OCD has related to their obsessions. For example, if a person with OCD asks a spouse, “Do you really love me?” the spouse should not feel the need to keep reassuring the person of their love. While this seems harsh if a person really needs that reassurance, maybe there is another issue with the relationship. An individual with OCD does not have any reason to ‘doubt’ love, for example, so reassuring that person will not help over the long run. What we feed grows stronger. Reducing reassurance works best gradually, with a plan from the therapist and a warm, supportive response instead of an answer.
It is advised that family members or close friends seek at least one session with a counselor who can help them understand what will be considered helpful.
Other Resources
- Expert Q&A from APA
- Read a Client Story from APA
- International OCD Foundation
- Journal Articles: references and abstracts from MEDLINE/PubMed (National Library of Medicine).
- OCD Statistics: Adults: information on the prevalence of OCD among adults.
Common Questions About OCD
Below are common questions which are frequently asked.
Can my awful thoughts and images be treated?
The short answer is YES, they can. Even that one in your mind that you would rather not share with even yourself.
One major hurdle individuals have in getting treated is that they are scared or embarrassed to share their thoughts. Even as I share this with you, perhaps you’re thinking, yes, but you’ve not heard “my” particular thought. Yes, that is true; however, there are a few things I hope I can help you understand:
- You’re not your thoughts. You’re not bad because you have any particular kind of thoughts or images passing through your mind.
- It would be right in line with what the OCD wants you to feel – after all, who or what ‘wants’ to be annihilated? It will try to convince you that ‘maybe’ something will happen to you if you share your deepest, darkest thoughts with your therapist.
- As a therapist, the content of your thought does not make a difference in your treatment.
- Having an intrusive thought is not the same as intending to act on it. I will not be calling the police or child services just because you told me you have certain fears or worries. I’m here to help you. But if you don’t share, I can’t help. (The legal limits of confidentiality, such as a real risk of harm, are explained in your first session.)
- Everyone has the same kinds of thoughts. The only difference is we need to help your brain rewire the kind of responses it gives to those same kinds of thoughts.
Is OCD inherited, or how did I get OCD?
Research shows that OCD does run in families and that genes play a role in the development of the disorder. Despite genes playing a role, it is also believed that there is probably a combination of genetic susceptibility and environmental and social influences.
The reason for your developing OCD will be hard to identify, but it is believed that symptoms may have always been there or so subtle that the disorder was undetectable. Chances are there was a predisposition already present, then a stressor came along which triggered the symptoms you’re experiencing.
When does OCD develop?
OCD can develop at any age, from childhood into adulthood. The average age at which symptoms begin is about 19, and OCD often starts earlier in males, with about a quarter of males showing symptoms before age 10.
How did I get OCD?
There is no one explanation for why you developed OCD. Chances are there was a predisposition already present.
Sometimes when something stressful happens in the life of a person who already has a predisposition to OCD, the symptoms may worsen or become evident for the first time.
While we won’t know definitively why your symptoms may be appearing, the good news is that we don’t “need” to know in order to treat it. That “need” to know can sometimes become obsessive, and if so, we’ll surely know that upon assessment.
Is OCD curable?
OCD is usually considered a long-term condition rather than one that is “cured,” but with treatment, many people reach a point where symptoms no longer create distress or are barely noticeable. You will also learn how to effectively deal with times in your life when new or old obsessions start to become an issue for you.
People who are prone to anxiety may notice it return at stressful times in life, but anxiety is very treatable, and one can learn effective means of coping and solving related issues.
Additionally, reducing stressors and taking care of your basic needs, like eating a balanced diet, exercising, sleeping properly, and engaging in regular self-care, can reduce triggers.
Keep Reading
You don’t have to stay on the think-about
Book a free 15-minute meet & greet to ask your questions and see whether working with Dr. Aisha is the right fit.
Book a Free Meet & GreetDisclaimer
None of the information on this website is intended to diagnose or treat any condition. This information is for educational use only. Please get treatment if you feel you are struggling with different symptoms. If you are in crisis, call or text 988 (in the US), call your local emergency number, or go to the nearest emergency room.